Dementia Today
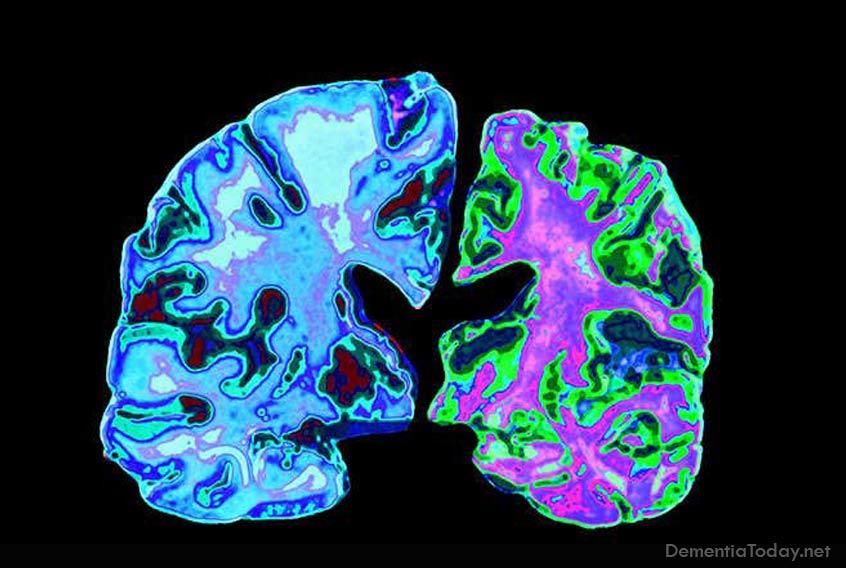
An important advance in the evaluation of people with suspected dementia of the Alzheimer type is the use of structural imaging to assess in vivo neuroanatomical changes. This technique can also be used in conjunction with neuropsychological test data to better understand the relationship between the structural brain changes and the cognitive deficits that characterize the disease.
Hippocampus
Integrity of the hippocampus has been strongly implicated in episodic memory (Squire 1992). Magnetic resonance imaging studies indicate substantial hippocampal atrophy in DAT, even in the very early stages of the disease (Jack et al. 1992; Scheltens et al. 1992; Killiany et al. 1993; Laakso et al. 1995; Johnson et al. 1998). In contrast, the hippocampus is spared significant aging effects through the seventh decade of life in healthy normals (Bigler et al. 1997). Studies of hippocampal atrophy in patients and healthy controls have reported agerelated volume changes (i.e., greater volume loss with increased age) only in healthy controls. In contrast, in persons with MCI and DAT, volume reductions were not related to age (de Leon et al. 1997; de Toledo-Morrell et al. 1997). Although minimal longitudinal data are available, Jack, Petersen, and Xu (1998, 2000) reported significant annual decline in hippocampal volume in healthy older adults; persons with MCI showed somewhat greater rates of decline, while persons with DAT showed the greatest decline. Furthermore, within the control and MCI groups, clinical decline was related to greater rates of hippocampal atrophy.
Several studies have examined the relationship between hippocampal volume and cognitive functioning.
For example, de Leon et al. (1997) found that after controlling for age, education, and immediate memory, a significant correlation was found between delayed memory and hippocampal atrophy in normal controls, but not in individuals with MCI (subjects with DAT were too impaired to be studied). In contrast, Convit et al. (1997) reported a relationship between delayed memory function and hippocampal volume in both healthy controls and persons with MCI. This may reflect the degree of impairment in the population with MCI in the de Leon study, since these relations become harder to detect as cognitive impairment becomes more severe. General cognitive measures such as the MMSE did not distinguish between normal controls and participants with MCI, and had no relationship to hippocampal volume. This lack of association has also been reported in persons with DAT (de Toledo-Morrell et al. 1997). Wilson et al. (1996) reported that hippocampal formation volume was associated with a delayed recall measure, but not with immediate recall, and with an object-naming test in persons with DAT. Medial temporal region volumes have been found to be correlated with delayed memory performance in persons with DAT (Kohler et al. 1998) and in elderly individuals without dementia (Golomb et al. 1994; Convit et al. 1997).
- Normal Aging & Dementia
- Concepts and Criteria
- Normal Aging
- Age-associated Memory Impairment
- Age-associated Cognitive Decline
- Mild Cognitive Impairment
- Diagnose dementia
- Cognition and Cognitive Testing
- Memory Impairment
- Executive Ability
- Visuospatial/Constructional and Visuoperceptual Abilities
- Praxis
- Neuroanatomy
- Structural Imaging
- Hippocampus
- Entorhinal Cortex
- Other Structural Changes
- Functional Imaging
- Functional Activation Studies
- Clinical Conclusions
- Acknowledgments
Entorhinal Cortex
Recent evidence strongly suggests that one of the earliest changes in dementia of the Alzheimer type is neurofibrillary tangles in the entorhinal cortex (Braak, Braak, and Bohl 1993). Measurement of the entorhinal cortex may provide a useful marker for early diagnosis (Bobinski et al. 1999). MRI studies show significant reductions of entorhinal cortex volume in DAT (Pearlson et al. 1992; Desmond et al. 1994; Juottonen et al. 1998; Krasuski et al. 1998). Entorhinal cortex volume is reduced even in persons with MCI compared to controls on MRI (Xu et al. 2000) and postmortem evaluation (Kordower et al. 2001). Baseline volumes of the entorhinal cortex predict conversion from MCI to DAT (Fox et al. 1996; Jack et al. 1999; Killiany et al. 2000). Juottonen et al. (1998) reported a significant correlation between left entorhinal cortex volume (corrected for whole brain size) and MMSE scores in persons with DAT.
Other Structural Changes
Other investigators have demonstrated the importance of measuring whole brain volume (Fox and Rossor 1999; Fox, Warrington, and Rossor 1999) to differentiate dementia of the Alzheimer type from healthy controls. White matter lesions (Barber et al. 1999; Wolf et al. 2000; DeCarli et al. 2001; Farkas and Luiten 2001) and metabolite changes (for review, Valenzuela and Sachdev 2001) may also be helpful for distinguishing between healthy controls and individuals with MCI and DAT. These measures may prove to be useful early indicators of conversion from MCI to DAT.
In summary, quantitative structural neuroimaging has revealed prominent and progressive cortical atrophy in dementia of the Alzheimer type starting in the earliest stages of the disease, with particular involvement of mesial temporal structures including entorhinal cortex and hippocampus observed even in mild cognitive impairment. In clinical practice, detailed evaluation of MRI findings in very mild cases may be of particular interest for early diagnosis (Soininen et al. 1994; Parnetti et al. 1996; Convit et al. 1997, 2000; de Toledo-Morrell et al. 1997; Jack et al. 1997). A promising new direction in structural neuroimaging of MCI and DAT is voxel-based morphometry (Ashburner and Friston 2000; Chung et al. 2001), a technique involving analysis of white matter, and cerebrospinal fluid tissue compartments on a voxel-by-voxel basis. Voxel-based morphometry may increase the clinical applicability of volumetric assessment in the early detection of at-risk individuals and those with early stages of dementia. Other promising techniques include functional neuroimaging methods.
###
Laura A. Flashman, Ph.D.,
Heather A. Wishart, Ph.D.,
Thomas E. Oxman, M.D.,
and Andrew J. Saykin, Psy.D.
###
REFERENCES
- Kral, V.A. 1958. Neuro-psychiatric observations in an old peoples home. Journal of Gerontology 13:169-76.
- Kral, V.A. 1962. Senescent forgetfulness: Benign and malignant. Canadian Medical Association Journal 86:257-60.
- Krasuski, J.S., G.E. Alexander, B. Horwitz, et al. 1998. Volumes of medial temporal lobe structures in patients with Alzheimer’s disease and mild cognitive impairment (and in healthy controls). Biological Psychiatry 43 (1):60-68.
- Kuhl, D.E., R.A. Koeppe, S. Minoshima, et al. 1999. In vivo mapping of cerebral acetylcholinesterase activity in aging and Alzheimer’s disease. Neurology 52:691-99.
- Laakso, M.P., H. Soininen, K. Partanen, et al. 1995. Volumes of hippocampus, amygdala and frontal lobes in the MRI-based diagnosis of early Alzheimer’s disease: correlation with memory functions. Journal of Neural Transmission, Parkinson Disease and Dementia Section 9 (1):73-86.
- Lange, K.W., B.J. Sahakian, N.P. Quinn, et al. 1995. Comparison of executive and visuospatial memory function in Huntington’s disease and dementia of Alzheimer type matched for degree of dementia. Journal of Neurology, Neurosurgery, and Psychiatry 58 (5):598-606.
- Lauter, H. 1985. What do we know about Alzheimer’s disease today? Danish Medical Bulletin 32 (Suppl. 1):S1-21.